 LINGCORE SCI
Ordinal Logistic Regression in Clinical Research: Modeling Ordered Outcomes Without Throwing Away Information
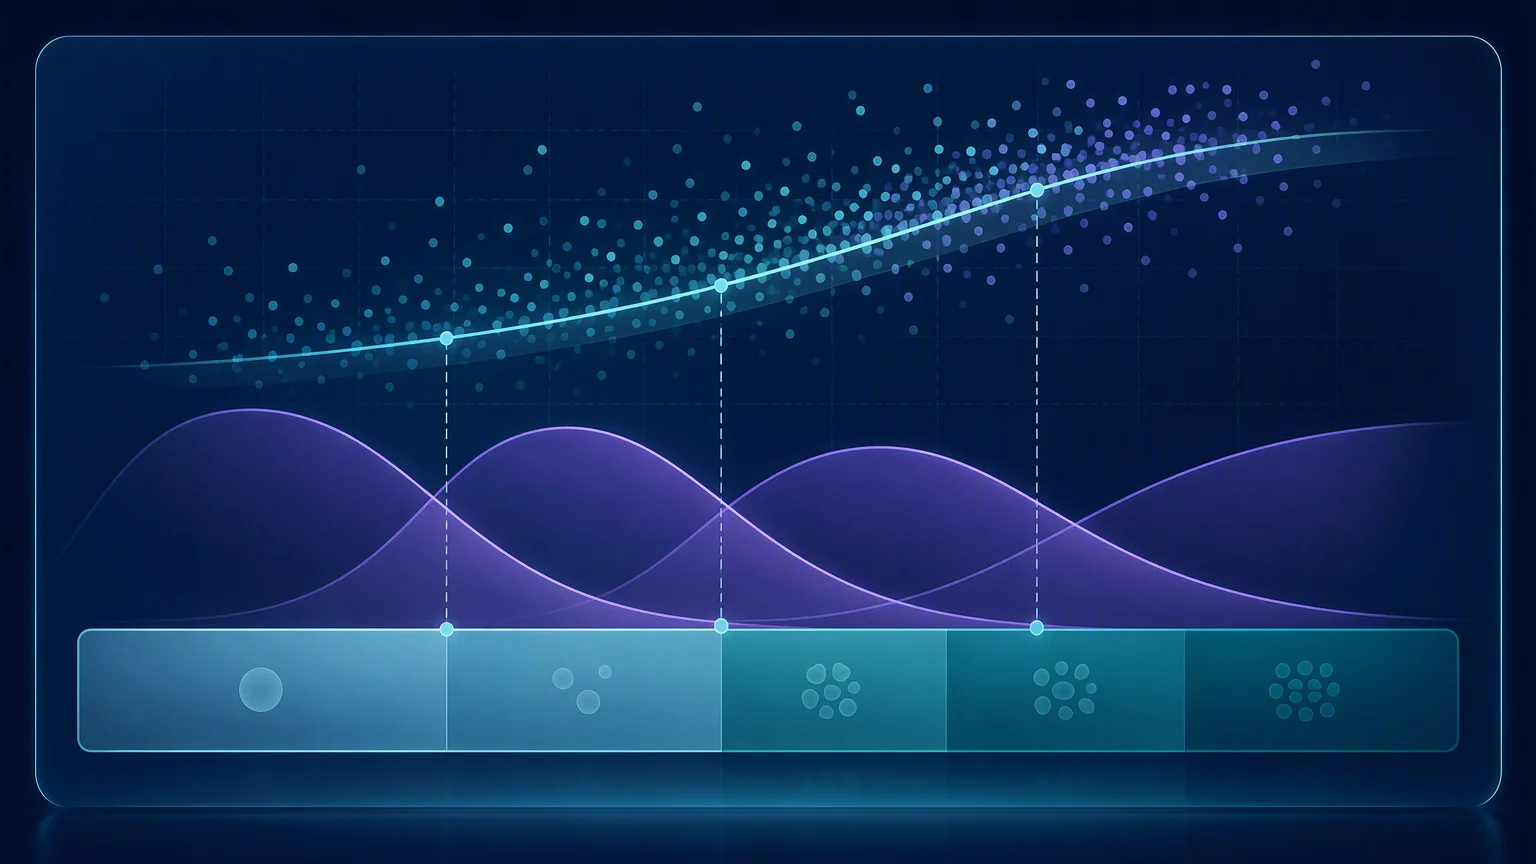
Ordinal logistic regression models ordered categories such as none, mild, moderate, and severe without treating the gaps between categories as equal. The proportional-odds model summarizes a predictor’s association across cumulative cut points with one coefficient, but that assumption must be checked; when effects differ by cut point, a partial proportional-odds or another ordinal model is more appropriate.
Many clinical outcomes are not naturally binary. A neurologic disability scale, symptom severity grade, radiologic response category, functional class, or patient-reported rating may contain several ordered levels. The order carries information: severe disease is not merely a different label from mild disease. Yet the distance between mild and moderate is not necessarily the same as the distance between moderate and severe.
A common shortcut is to collapse the outcome into two groups and fit binary logistic regression. That can be reasonable when the clinical question is explicitly binary, but it may discard information when the original ordering is meaningful. Ordinal logistic regression provides another route. It models cumulative thresholds between categories and preserves the order without pretending that the categories form an equally spaced numerical scale.
The most familiar version is the cumulative-logit proportional-odds model. Its appeal is concise interpretation: one predictor coefficient can describe the shift toward higher or lower outcome categories across several cumulative splits. Its risk is equally important: the common-effect assumption is substantive and must be evaluated rather than accepted because software returns a coefficient.
What makes an outcome ordinal?
An ordinal outcome has categories that can be ranked, but the categories do not have to be equally spaced. Examples include no/mild/severe injury, ordered response grades, functional disability scales, and disease stages. The scale may have clinical meaning without supporting arithmetic operations such as calculating an average score that treats each step as identical.
Ordinal and nominal outcomes are different. A nominal outcome has categories without a meaningful order, such as different pathogen types or unrelated diagnostic groups. A multinomial model may be appropriate for nominal categories. An ordinal model is appropriate only when the ordering is clinically or scientifically defensible.
Before modeling, investigators should define the category order, verify whether the scale is truly ordinal, document how ambiguous or collapsed categories were handled, and decide whether the research question concerns a global shift across the scale or a particular threshold. The model should follow the clinical question rather than the availability of a default software option.
How the cumulative-logit model works
Suppose an outcome has four ordered levels, from least to most severe. A cumulative-logit model considers thresholds such as the odds of being at or above level 2, at or above level 3, and at or above level 4. The model estimates how a predictor changes those cumulative odds while preserving the ordering of the thresholds.
In the proportional-odds form, the predictor effect is constrained to be the same across cumulative cut points, while each cut point has its own intercept or threshold. The common odds ratio is therefore a cumulative odds ratio. Depending on how the outcome and predictor are coded, an odds ratio above one may indicate greater odds of being in a higher category or greater odds of being at or below a category. Coding direction must be stated explicitly.
The cumulative odds ratio is not the probability of a specific category. It also does not mean that the absolute probability of severe disease changes by the same amount for every patient. To make the result clinically interpretable, report predicted probabilities for each category at representative covariate values, with confidence intervals or uncertainty intervals where appropriate.

The proportional-odds assumption is a clinical assumption
The proportional-odds or parallel-slopes assumption states that a predictor has the same log-odds effect across the cumulative splits. In practical terms, the predictor is assumed to shift the distribution along the ordered outcome scale in a broadly consistent way rather than having one effect for mild versus moderate disease and another for severe disease.
This assumption can be plausible, but it should not be treated as automatic. A statistical test may be sensitive to sample size, and a non-significant result does not prove that the assumption is clinically correct. Investigators should combine diagnostics with subject-matter reasoning, inspect category-specific estimates, examine predicted probabilities, and consider whether the effect could reasonably differ at different thresholds.
When proportional odds is not credible, several options are available. A partial proportional-odds model can retain common effects for some predictors while allowing other predictors to vary by cut point. Alternative ordinal models include adjacent-category logits and continuation-ratio models, each of which changes the comparison being modeled. A multinomial model may be used when the ordering is not defensible, but it generally uses more parameters and gives up the efficiency or interpretation gained from the order.
Ordinal logistic regression versus common alternatives
Model choice depends on what the investigator wants to compare. Collapsing the outcome into a binary endpoint may be the most transparent choice when a single threshold defines the clinical decision. It becomes less attractive when the threshold is arbitrary or when lower and higher categories both matter. A multinomial model avoids ordering assumptions but treats the categories as unrelated in the model structure. Ordinal models use the order and therefore need assumptions about how the predictor operates across categories.
| Approach | What it preserves | What it assumes or sacrifices | When it fits |
|---|---|---|---|
| Binary logistic after dichotomization | One prespecified clinical threshold. | Discarded information below and above the chosen threshold; threshold choice must be justified. | One binary decision is the primary estimand. |
| Multinomial logistic | Separate category comparisons without ordering. | Does not use the ordering; can require many parameters. | Categories are nominal or ordering is not scientifically defensible. |
| Proportional-odds ordinal model | Category ordering with one common predictor effect across cumulative cut points. | Requires proportional odds; a single effect can hide threshold-specific differences. | A global shift across ordered categories is clinically meaningful and assumption is plausible. |
| Partial proportional odds | Ordering while allowing selected predictors to vary by cut point. | More parameters and more complex interpretation; structure must be specified carefully. | Some predictors violate the common-effect assumption. |
| Adjacent-category or continuation-ratio model | Ordered transitions or neighboring category comparisons. | Targets a different scientific question than cumulative odds. | Progression, stage transition, or adjacent-level processes are central. |
Do not confuse ordinal outcomes with numeric scores
Researchers sometimes use linear regression for an ordinal scale because it has several numeric levels. That can be acceptable in selected settings, especially when the scale behaves approximately continuously and the estimand is clearly defined, but the assumption should be defended. Equal numerical spacing is not guaranteed by the presence of numbers in the category labels.
At the other extreme, dichotomizing every ordinal outcome can make a manuscript easier to summarize but can reduce precision, lower power, and hide clinically relevant shifts between neighboring categories. In biomarker studies, retaining the ordinal outcome may improve the construction or selection of predictor combinations in settings where the disease severity levels carry useful information.
The right comparison is not “ordinal models are always better.” The right question is whether the analysis matches the clinical decision. If clinicians act when a patient reaches severe disease, a severe-versus-not-severe estimand may be primary, with the full ordinal outcome as a secondary analysis. If a treatment is expected to shift the entire disability distribution, an ordinal model may provide a more efficient and clinically coherent summary.
Clinical examples of ordered outcomes
Neurologic studies often use ordered disability scales such as the modified Rankin Scale. Kidney injury research may distinguish no injury, mild injury, and severe injury. Oncology studies may classify response or disease grade across ordered levels. Patient-reported outcome instruments may have ordered response categories, but their measurement properties and category interpretation require attention.
In each example, investigators should state whether the outcome is used for explanation, prediction, treatment comparison, or biomarker selection. A model that predicts severe disease may need category-specific discrimination and calibration, while a trial analysis may focus on a common odds ratio or a treatment-induced shift. The same ordinal scale can support different estimands.
Published biomarker methodology illustrates why preserving ordinal information can matter. When an outcome contains no, mild, and severe disease levels but the clinical interest centers on severe disease, simply dichotomizing the outcome can lose information during biomarker construction or candidate-combination selection. An ordinal-aware strategy can use the broader outcome structure while still evaluating the clinically important level.
Actionable Steps: Plan and report an ordinal model
| Step | Research action | Quality gate |
|---|---|---|
| 1. Define the ordered estimand | State the outcome order, clinical meaning of each category, primary threshold or global shift, and coding direction. | Categories are ordered by clinical logic, not only by database labels. |
| 2. Choose the model family | Compare cumulative-logit, partial proportional-odds, adjacent-category, continuation-ratio, multinomial, or binary models against the research question. | The selected model answers the intended clinical comparison and its assumptions are explicit. |
| 3. Check proportional odds | Use diagnostics, category-specific estimates, predicted probabilities, and subject-matter reasoning to assess the common-effect restriction. | Violations trigger partial proportional odds, an alternative model, or a transparent limitation. |
| 4. Report interpretable effects | Give cumulative odds ratios with confidence intervals, coding direction, threshold estimates, and predicted probabilities for representative profiles. | Readers can distinguish a cumulative association from a category-specific probability change. |
| 5. Validate and stress-test | Assess calibration, discrimination where relevant, category imbalance, missingness, collapsing sensitivity, and alternative model specifications. | The conclusion is not dependent on one arbitrary cut point or one untested model restriction. |
Common reporting failures
The first failure is collapsing an ordered outcome without explaining the clinical threshold. If the threshold was selected after looking at treatment effects or model performance, the resulting estimate may be optimistic and difficult to reproduce.
The second failure is presenting an odds ratio without stating whether it refers to being at or above, or at or below, each cumulative threshold. Reversing the category coding can reverse the clinical interpretation while leaving the absolute value of the odds ratio unchanged.
The third failure is reporting a proportional-odds model without any assessment of the common-effect assumption. Software output is not an assumption check. At minimum, explain the diagnostic approach, show whether threshold-specific patterns were considered, and state what was done when the assumption was questionable.
The fourth failure is treating ordinal categories as equally spaced measurements without a measurement argument. A five-level scale does not automatically justify linear regression or a mean difference interpreted as one equal unit of clinical improvement.
The fifth failure is interpreting the cumulative odds ratio as a probability of severe disease. Predicted category probabilities are needed when clinical decisions depend on a particular severity level.
The sixth failure is selecting the most complex ordinal model without enough information to support it. Partial proportional odds and flexible alternatives can be useful, but added parameters require adequate sample size, clear specification, and validation.
Evidence Summary Table
| Evidence or methods source | What it supports | Level and boundary |
|---|---|---|
| Bender & Grouven Medical methods tutorial | Introduces proportional-odds modeling for ordered outcomes and its relationship to binary logistic regression. | Methods tutorial; coding and model assumptions remain study-specific. |
| Armstrong & Sloan, 1989 Epidemiologic methods | Reviews ordinal regression models for epidemiologic data and proportional-odds reasoning. | Foundational methodology; report the estimand and assumption checks. |
| Ananth & Kleinbaum, 1997 Methods review | Reviews regression models and applications for ordinal responses. | Review; different ordinal models answer different questions. |
| Bender & Grouven, 1998 Non-proportional odds | Discusses binary logistic approaches and non-proportional odds for ordinal data. | Methods paper; partial proportional-odds alternatives need careful specification. |
| Yu et al., 2018 Open-access biomarker methodology | Shows how ordinal outcomes can inform biomarker construction and selection; dichotomization may discard information. | Applied methodology; gains depend on outcome structure and prediction target. |
| Risselada et al., 2010 Neurologic prediction application | Illustrates ordinal prediction for an ordered neurologic disability outcome. | Clinical application; prediction performance and validation remain necessary. |
Researcher's Toolkit: Audit an Ordinal Outcome Analysis
Use Lingcore SCI tools to organize and quality-check ordinal regression research:
- Paper Analyzer: Extract outcome ordering, category definitions, coding direction, proportional-odds diagnostics, predicted probabilities, and validation metrics.
- Review Builder: Build a citation-linked comparison of cumulative-logit, partial proportional-odds, multinomial, and binary approaches.
- Journal Matcher: Compare journals publishing clinical prediction, biomarkers, epidemiology, outcomes research, and biostatistical methodology.
These tools support evidence organization and reporting quality. Researchers remain responsible for the estimand, model assumptions, missing-data handling, validation, clinical interpretation, and regulatory or institutional review.
Conclusion
Ordinal logistic regression is useful when clinical categories have a meaningful order but not necessarily equal spacing. The proportional-odds model can provide a compact cumulative effect estimate, while predicted category probabilities make the result easier to interpret clinically. The central requirement is not to use the most complex model; it is to choose a model whose estimand and assumptions match the outcome and decision.
A credible ordinal analysis defines the category order, justifies the model family, checks proportional odds, reports coding direction and uncertainty, and evaluates sensitivity to alternative specifications. When the common-effect assumption fails, partial proportional odds or another model may be more honest than forcing one odds ratio across all thresholds.
Medical Disclaimer
This article is for medical research and educational purposes only. It does not provide medical advice, diagnosis, treatment recommendations, or a substitute for clinical, statistical, regulatory, or institutional review. Researchers must verify the cited sources, outcome definitions, model assumptions, diagnostics, and validation results before using ordinal regression in a study or decision.